For administrators
Evidence you can act on.
A median length of stay tells you how long patients waited. OmniFlowED tells you which of six failure modes caused the wait, on which shift, in which zone, recorded by the physicians standing in it.
What the overview answers
Where is the time going?
Delays ranked by contributing factor and by category, with average duration per category, so a single view distinguishes a radiology staffing problem from an inpatient capacity problem.
Where and when?
Breakdowns by zone and by shift. Bottlenecks are rarely uniform across a department or a day, and a fix aimed at the average misses both.
What keeps happening?
Physicians flag delays they have seen before. The recurring count turns "this happens every weekend" into a number you can bring to a capacity meeting.
Why physicians will actually use it
Adoption is the whole problem. A reporting tool that feels like a complaint form, a chart task, or a way to name a colleague gets abandoned inside a month. Two product rules are what prevent that.
- Non-punitive by construction. There is no per-clinician view to ask for, so nobody has to trust a policy.
- Attribution is the reporter’s choice, report by report. Anonymous entries carry the same analytic weight.
- Two screens, controlled lists. Filing a delay costs less attention than the hallway conversation it replaces.
Why governance is short
The dataset contains no protected health information, by design rather than by configuration. That removes most of what usually makes a new clinical tool slow to approve.
- No patient identifiers to review. A case is a zone, a room and two timestamps.
- No EHR integration. Nothing to scope, nothing to interface, no chart read or write.
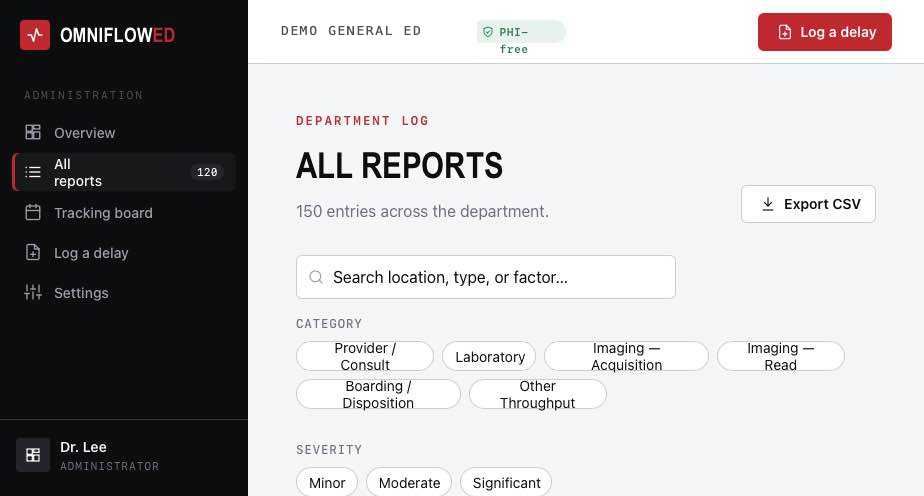
- Your data leaves as CSV, on request, at any time, pilot or not.
Nothing to procure.
No purchase order, no EHR integration, no IT project. Your zone and room layout is the whole configuration, the pilot is free while you run it, and the dataset exports to CSV whether you continue or not.